Conditions · Face · Breakouts That Aren't Acne

Fungal Acne (Malassezia Folliculitis)

Medically reviewed by Dr Sin Yong · Last reviewed · 12 min read · Assessed personally by Dr Sin Yong · Jump to questions

“Fungal acne” is not acne at all. It is folliculitis caused by Malassezia — a yeast that lives on everyone's skin — overgrowing inside the hair follicle. Because the bumps mimic acne almost perfectly, it is routinely treated with acne medication, which does nothing and sometimes makes it worse.

WhatsApp Dr Sin Yong →
Invited by Device Makers to Share His Expertise
International KOL for 14+ device brandsShared his clinical expertise with 500+ doctors across AsiaMBBS (NUS) · MRCS (Edinburgh) · MSc with Distinction (Queen Mary, London) · MSc (Cardiff)Every assessment personally by Dr Sin Yong

Fungal acne treatment means treating a yeast, not bacteria. Malassezia folliculitis is usually managed with topical antifungal washes and creams, with oral antifungal medicine reserved for extensive or stubborn cases after a doctor's assessment and prescription. Acne antibiotics do not target the yeast, and because Malassezia is part of normal skin flora, maintenance matters.

In brief
  • Fungal acne is Malassezia folliculitis, a yeast overgrowth inside hair follicles, not true acne.
  • It typically shows as uniform, often itchy small bumps on the forehead, hairline, chest, shoulders and back.
  • Acne products and antibiotics target bacteria, so they do not treat a yeast and can sometimes worsen it.
Key takeaways
  • Fungal acne is Malassezia folliculitis, a yeast overgrowth inside hair follicles, not true acne.
  • It typically shows as uniform, often itchy small bumps on the forehead, hairline, chest, shoulders and back.
  • Acne products and antibiotics target bacteria, so they do not treat a yeast and can sometimes worsen it.
  • Treatment is usually topical antifungal; oral antifungal medicine is reserved for extensive or stubborn cases after prescription.
  • Malassezia is part of normal skin flora, so control and maintenance matter more than a one-off clearance.

Key Facts

The organism
Malassezia — a lipophilic (oil-feeding) yeast, part of normal skin flora
Where it lives
Inside the follicle, feeding on sebum and fatty acids
Classic distribution
Forehead and hairline, chest, shoulders, upper back — sites rich in sebaceous follicles
The giveaway sign
Monomorphic bumps — dozens of near-identical 1–2 mm papules and pustules, often itchy
Climate factor
Heat, humidity and occlusion drive overgrowth — Singapore's baseline weather
Why antibiotics fail
Antibacterials do not kill yeast; suppressing bacteria can hand the follicle to Malassezia
Who assesses this
An aesthetic physician or dermatologist — clinical diagnosis, sometimes microscopy
Typical first step
Stop stacking acne products; get the organism identified first

What does fungal acne look like?
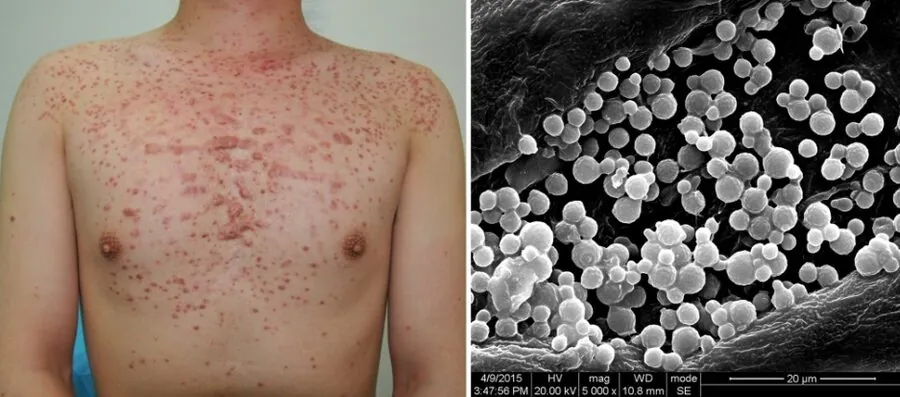
Malassezia (fungal) folliculitis of the trunk, with the yeast shown on electron microscopy
Malassezia (fungal) folliculitis of the trunk, with the yeast shown on electron microscopy. Image: Ran Yuping et al., via Wikimedia Commons (CC BY-SA 3.0).
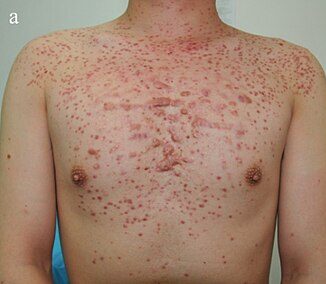
Monomorphic papules over the chest
Monomorphic papules over the chest. Image: Ran Yuping et al., via Wikimedia Commons (CC BY-SA 3.0).
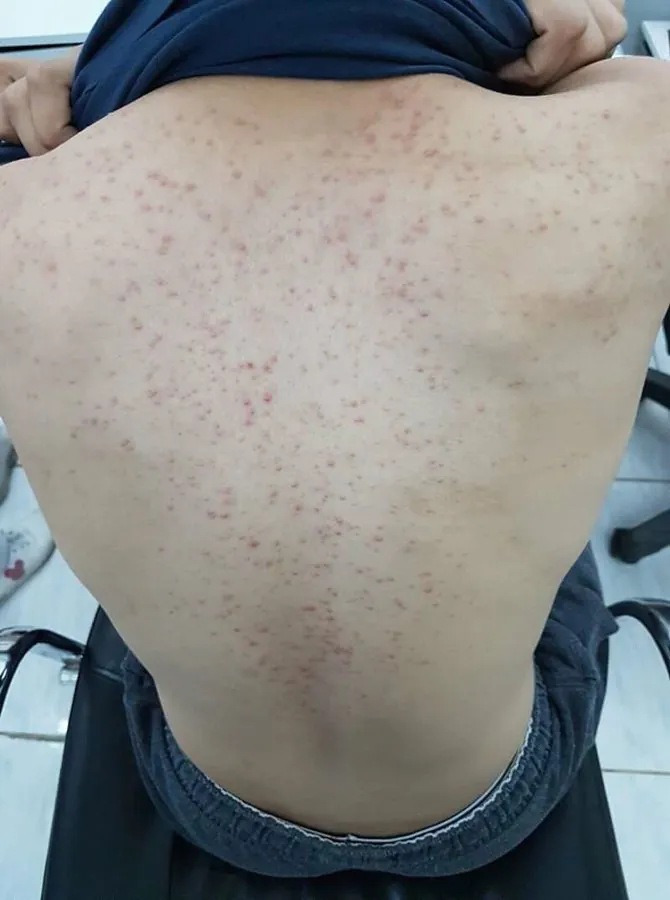
Uniform itchy papules across the back
Uniform itchy papules across the back. Image: Mohammad2018, via Wikimedia Commons (CC BY-SA 4.0).

Why does fungal acne look like acne but behave differently?

True acne vulgaris is a disease of the pilosebaceous unit involving comedones, Cutibacterium acnes and inflammation — and its lesions are polymorphic: blackheads, whiteheads, papules and deeper nodules of different ages coexisting. Malassezia folliculitis is a different process: yeast proliferating within the follicle triggers inflammation that surfaces as crops of strikingly uniform, often itchy papulopustules. Recent reviews describe it as one of the most common mimickers of acneiform eruptions, and one of the most underdiagnosed [1,2]. The itch, the uniformity and the distribution — forehead, chest, back rather than cheeks and jaw — are the pattern a physician reads.

Why your acne routine never worked

This is the condition behind years of failed skincare. Benzoyl peroxide and topical antibiotics target bacteria; Malassezia is a yeast. Long courses of oral antibiotics can actually worsen it by suppressing the bacterial flora that normally compete with the yeast [1,3]. Meanwhile heavy, oil-based moisturisers and sunscreens feed the organism — Malassezia metabolises exactly the lipids many products are built on. If your “acne” flares with sweat, occlusive gym wear or thick skincare and laughs at every acne product you have tried, the diagnosis deserves a second look.

What actually works for fungal acne?

Antifungal treatment — topical antifungal washes and creams, with oral antifungals reserved for extensive or stubborn cases under physician supervision [1,3]. Because Malassezia is part of normal skin flora, the honest framing is control rather than eradication: recurrence in a hot, humid climate is common and maintenance matters. And because true acne and Malassezia folliculitis frequently coexist in the same patient, both arms may need treatment — the acne programme and back acne page cover how Dr Sin Yong sequences this. Diagnosis comes first: treating the wrong organism for another year is the real cost.

What doesn't work for fungal acne?

Scrubbing — the yeast is inside the follicle, not on the surface. “Antibacterial” soaps — wrong kingdom. Stacking more acne actives — irritation without effect. And self-prescribed long-term oral antibiotics are the classic way this condition digs in. If a breakout is itchy, uniform and antibiotic-resistant, stop adding products and get it diagnosed.

“If every acne product has failed and the bumps itch, the question is not which acne treatment is next — it is whether this is acne at all.”

— Dr Sin Yong

Dr Sin Yong’s Viewpoint

Some of the most relieved patients in my clinic are the ones told their 'acne' was never acne. Years of benzoyl peroxide against a yeast — of course it failed. If your breakout itches, sits uniform across the forehead, chest or back, and laughs at acne products, ask for a diagnosis before another routine. The organism decides the treatment.

Prefer Not to Use WhatsApp?

Use the short enquiry form instead →

Leave your name, mobile number and email and the clinic will contact you directly. No obligation.

Your details are delivered directly to Dr Sin Yong's clinic team.

Thank you — your enquiry has been received. The clinic will contact you during opening hours (Mon–Fri 10am–8pm, Sat 11am–3pm).

Prefer a preliminary view first? You can also WhatsApp a photo of the area for Dr Sin Yong to review before you decide on a visit.

Which type do you have?

Fungal acne and the conditions it is mistaken for
Type / look-alikeHow to recognise itWhat it needsWhat does not work
Malassezia folliculitis (fungal acne)Near-identical itchy small bumps on forehead, chest, shoulders or backTopical antifungal, with oral antifungal for extensive or stubborn casesBenzoyl peroxide, antibacterial soaps and long antibiotic courses
True acne (acne vulgaris)Mixed blackheads, whiteheads, papules and deeper lesions, rarely itchyAcne treatment chosen by severity after assessmentAntifungal treatment alone when comedones and nodules are present
Acne and fungal acne togetherUniform itchy bumps alongside mixed acne lesions in the same personBoth arms treated, sequenced by a physicianOne-product routines aimed at only one cause
Bacterial folliculitis, a look-alikeTender, pus-topped bumps around hairs, often after shaving or frictionAssessment, then treatment directed at the bacteria involvedAntifungal wash used on the assumption of yeast
Seborrhoeic dermatitis, a look-alikeScaly, greasy, red patches around the nose, brows and scalp marginDiagnosis, then treatment for that conditionAcne actives, which irritate without helping

What does not work, and why

When to see a doctor

Myths we hear in clinic

“Fungal acne is caused by poor hygiene.”

It is an overgrowth of a yeast that everyone carries, driven by heat, humidity, oil and occlusion rather than dirt.

“A stronger acne routine will eventually clear it.”

Acne products act on bacteria, so adding more of them does not treat a yeast and may irritate the skin.

Questions Patients Actually Ask

How can I tell fungal acne from real acne?+

Uniformity, itch and location. Malassezia folliculitis produces near-identical small bumps, often itchy, on the forehead, chest and back. True acne is polymorphic — mixed blackheads, whiteheads and deeper lesions — and rarely itches. Confirmation is clinical, sometimes with microscopy.

Why did it get worse after antibiotics?+

Antibiotics suppress skin bacteria that compete with Malassezia. With the competition gone, the yeast can overgrow — a documented pattern in the literature.

Is fungal acne contagious?+

No. Malassezia lives on everyone's skin. The condition is an overgrowth in a susceptible follicle, not an infection you catch or pass on.

Does diet cause it?+

No good evidence links diet to Malassezia folliculitis. Heat, humidity, occlusion, oily skin and prior antibiotic use are the documented drivers.

Can fungal acne and normal acne exist together?+

Frequently — and this is why one-product routines fail. Each arm needs its own treatment, which is a physician's sequencing decision.

Will it come back?+

It can, because the yeast is a normal, lasting part of skin flora and Singapore's climate favours it. A maintenance plan — often as simple as a periodic antifungal wash — helps keep it under control.

Can I treat fungal acne at home with an antifungal shampoo?+
Some people use an antifungal shampoo as a short-contact wash on the face or body, and it is a common part of treatment, but it is worth confirming the diagnosis first. Several conditions mimic fungal acne, true acne often coexists with it, and an antifungal wash will not help a problem that is not Malassezia. A doctor can confirm what the bumps are and advise which product to use, how often and for how long.
How long does fungal acne treatment take to work?+
It varies between people and between areas. Response is usually reviewed after a few weeks of consistent treatment rather than judged after a few days. Because the yeast is part of normal skin flora, settling a flare is only part of the plan; a maintenance routine is often needed to keep it under control in Singapore's climate.
What skin care should I avoid if I have fungal acne?+
Heavy, oil-rich moisturisers, sunscreens and hair products tend to feed Malassezia, which metabolises many of the lipids such products are built on. Lighter, non-occlusive formulations are generally preferred, and changing out of sweaty clothing promptly helps. Ingredient lists vary widely, so it is worth bringing your current products to the assessment.
What causes fungal acne?+
Malassezia is a yeast that lives on everyone's skin and feeds on sebum. Overgrowth inside the follicle triggers inflammation. Heat, humidity, sweat, occlusive clothing, oily skin and previous antibiotic use are the recognised drivers, and Singapore's climate favours it. It is not caused by poor hygiene and it is not contagious.
Can fungal acne be fully cured?+
It can be brought under control, but Malassezia is a normal, lasting part of skin flora, so recurrence is common in a hot, humid climate. Treatment settles a flare, and a maintenance routine set by your doctor helps keep it controlled. Promising that it will never return would be inaccurate, so the plan includes review.
Which treatment suits fungal acne?+
It depends on the diagnosis and extent. Topical antifungal washes and creams are usually the starting point, while oral antifungal medicine is reserved for extensive or stubborn cases after assessment and prescription. If true acne coexists, it needs its own plan. Confirming the organism comes first, because treating the wrong one delays improvement.
How much does fungal acne treatment cost in Singapore?+
The fee depends on the extent and sites involved, whether microscopy or other tests are needed, the medicines prescribed, and whether true acne also needs treatment. A written quote is given at consultation, after Dr Sin Yong has examined the skin. The consultation also decides which diagnosis is likely before any plan is costed, and whether treatment is advised at all.

References

  1. Malassezia Folliculitis Presentation, Diagnosis, and Treatment: A Review of “Fungal Acne” — PubMed.
  2. Malassezia Folliculitis: An Underdiagnosed Mimicker of Acneiform Eruptions — Journal of Fungi (PMC).
  3. Malassezia (Pityrosporum) Folliculitis — DermNet NZ.
Fungal acne treatment options compared
OptionWhat it doesWhat it cannot doTypical recoveryWho it tends to suit
Topical antifungal wash (for example ketoconazole, selenium sulfide or zinc pyrithione)Applied as a short-contact wash to reduce Malassezia on the skin and at the follicle openingsMay not control extensive or deeper follicular involvement on its ownNot a procedure; possible dryness or irritationMild to moderate fungal acne, and maintenance in a hot, humid climate
Topical antifungal creamApplied to affected areas to reduce yeast overgrowthLess practical over large areas such as the whole backNot a procedure; occasional irritationSmaller, localised areas such as the forehead or hairline
Oral antifungal medicine (prescription only)Treats the yeast from within when involvement is extensive or has not responded to topical treatmentRequires a doctor's assessment and prescription, and is not suitable for everyone because of possible side effects and drug interactionsNot a procedure; reviewed by the prescribing doctorExtensive or stubborn cases, after diagnosis
Acne antibiotics (topical or oral)Target the bacteria involved in acne vulgarisDo not kill yeast, and long courses can make Malassezia folliculitis worseNot a procedureTrue acne where it coexists, within a planned acne treatment rather than for fungal acne itself
Benzoyl peroxide and other acne activesAct on acne bacteria and comedonesNot directed at Malassezia; stacking them on fungal acne adds irritation without effectNot a procedure; dryness or irritationAcne vulgaris; not a substitute for antifungal treatment
Lighter skin care and sweat managementReduces the oils, occlusion and trapped sweat that feed overgrowthDoes not treat established overgrowth on its ownNot a procedureEveryone with fungal acne, alongside antifungal treatment

Medically reviewed by Dr Sin Yong, MBBS (NUS), MRCS (Edinburgh) · Last updated 5 October 2026 · Editorial policy

Related reading
Follow Dr Sin Yong
InstagramTikTokYouTubeThreadsXLinkedInFacebook
Dr Sin Yong · Every assessment personally performed
WhatsApp Enquiry