Conditions · Body · Scars

Keloids & Hypertrophic Scars

Medically reviewed by Dr Sin Yong · Last reviewed · 10 min read · Assessed personally by Dr Sin Yong · Jump to questions

A hypertrophic scar is healing that overshot: raised, red, but confined to the original wound and often settling with time. A keloid is healing that never received the stop signal: scar tissue growing beyond the wound's borders, months or years after the injury, and — critically — prone to returning larger if simply cut out.

WhatsApp Dr Sin Yong →
Invited by Device Makers to Share His Expertise
International KOL for 14+ device brandsShared his clinical expertise with 500+ doctors across AsiaMBBS (NUS) · MRCS (Edinburgh) · MSc with Distinction (Queen Mary, London) · MSc (Cardiff)Every assessment personally by Dr Sin Yong

Keloids and hypertrophic scars are both raised scars caused by collagen overproduction. A hypertrophic scar stays within the original wound and often settles partly with time; a keloid grows beyond the wound's borders and tends to recur if simply cut out. Assessment of the borders and history decides the plan, which usually starts with silicone, pressure and corticosteroid injections.

Also called: raised scars, 疤痕疙瘩, 蟹足肿, ケロイド

In brief
  • Keloids and hypertrophic scars are raised scars from collagen overproduction; a keloid grows beyond the wound's borders, a hypertrophic scar does not.
  • Treatment usually starts with silicone, pressure and corticosteroid injections, decided by border and history.
  • Cutting a keloid out alone is a fresh wound in keloid-forming skin, and recurrence after excision alone is the documented norm.
Key takeaways
  • Keloids and hypertrophic scars are raised scars from collagen overproduction; a keloid grows beyond the wound's borders, a hypertrophic scar does not.
  • Border and history assessment decides the plan, which usually starts with silicone, pressure and corticosteroid injections.
  • Cutting a keloid out alone is a fresh wound in keloid-forming skin, and recurrence after excision alone is the documented norm.
  • Itch and pain are real features of active keloids and are reviewed as treatment progresses.
  • A physician, Dr Sin Yong, assesses the scar personally; surgery is considered only alongside adjuvant treatment.

Key Facts

The defining difference
Hypertrophic scars stay within the wound's borders; keloids invade beyond them
Who is prone
Strong genetic loading; markedly higher incidence in Asian and African skin types
High-risk zones
Earlobes, jawline, chest, shoulders, upper back — high-tension, high-recurrence real estate
Common triggers
Piercings, acne, BCG vaccination, minor surgery, sometimes trivial or unnoticed injury
Why excision alone fails keloids
Surgery is a fresh wound in skin that keloids — recurrence after excision alone is the documented norm
The evidence ladder
Silicone + pressure → intralesional corticosteroid ± 5-FU → laser adjuncts → excision only with immediate adjuvant therapy
Who assesses this
A physician — keloid vs hypertrophic changes the whole plan
Typical first step
Border and history assessment, then the injection-based ladder

What do keloids look like?
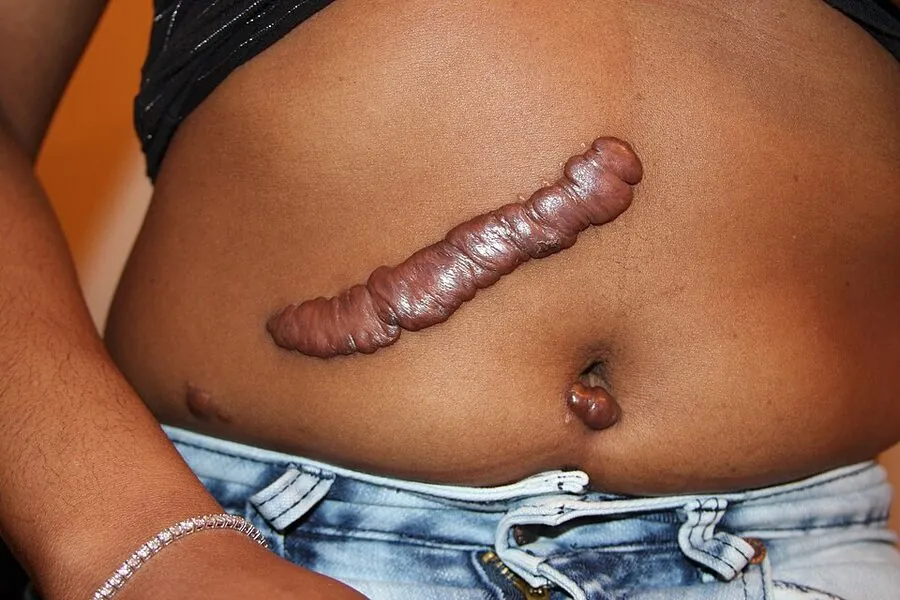
A keloid overgrowing the boundaries of the original surgical wound
A keloid overgrowing the boundaries of the original surgical wound. Image: Htirgan, via Wikimedia Commons (CC BY-SA 3.0).
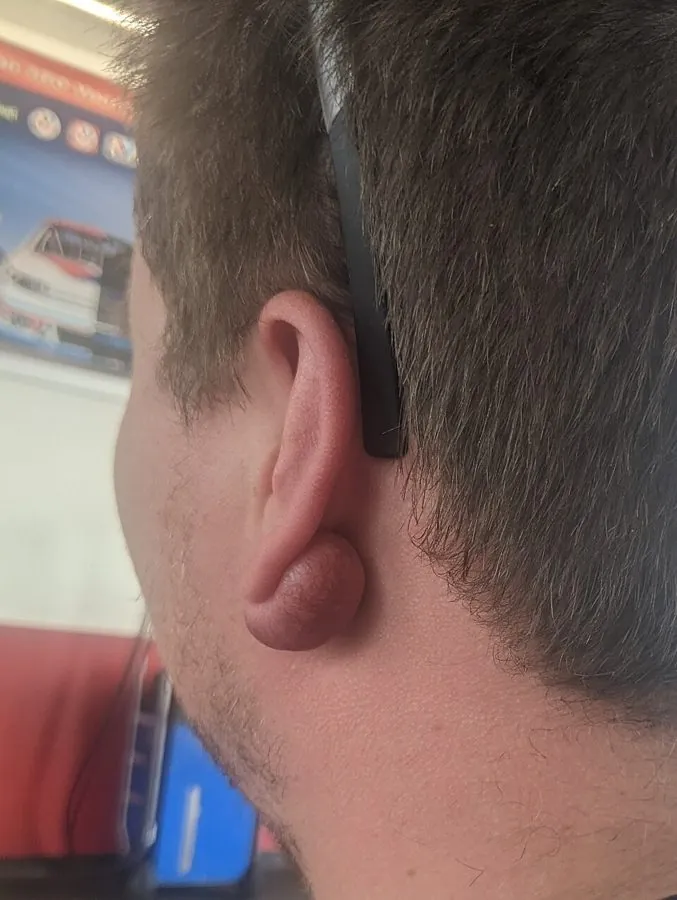
A keloid on the ear lobe after piercing
A keloid on the ear lobe after piercing. Image: Bobjgalindo, via Wikimedia Commons (CC BY 4.0).
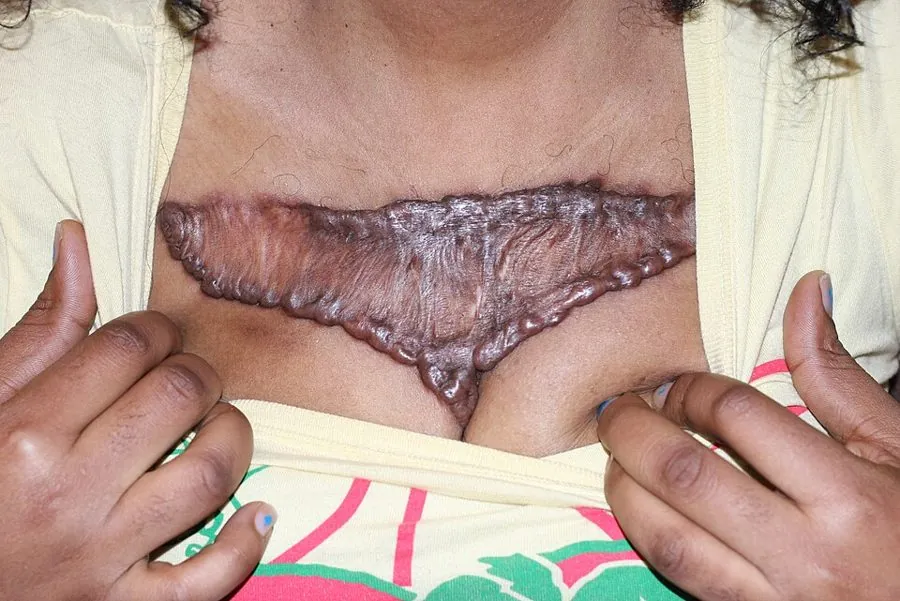
A large keloid across the chest wall
A large keloid across the chest wall. Image: Htirgan, via Wikimedia Commons (CC BY-SA 3.0).

Two overshoots, one spectrum

Both scars are collagen overproduction — fibroblasts that kept building after the repair was done. The international algorithms distinguish them by behaviour: hypertrophic scars rise within the wound, peak, and often regress partially over a year or two; keloids grow beyond the original borders, rarely regress, and can continue expanding for years [1]. Genetics deals the hand — keloid tendency runs in families and is substantially more common in Asian skin — and mechanical tension plays dealer, which is why the chest, shoulders and jawline lead the statistics while the eyelid almost never keloids.

Why is cutting a keloid off the classic mistake?

Excision alone answers a keloid with the one thing keloids love: a fresh wound in keloid-forming skin. The systematic reviews report high recurrence after solo excision — frequently with the new keloid outgrowing the old — which is why every modern algorithm permits surgery only with immediate adjuvant therapy: corticosteroid injection, pressure, silicone, and in selected cases superficial radiotherapy [1,2]. The same logic warns against casual procedures in keloid-prone patients: each piercing and elective excision on high-risk anatomy is a coin flip that should be an informed decision, not an accident.

What actually works for keloids?

A ladder, matched to the scar and climbed with patience [1,2]. Fresh, raised scars: silicone sheeting or gel with pressure — unglamorous, evidence-backed, and the base of every algorithm. Established scars: intralesional corticosteroid injections, the workhorse, softening and flattening over a course of sessions — combined with 5-fluorouracil in resistant disease. Vascular laser calms redness; fractional approaches help texture as adjuncts. Excision is reserved, always chaperoned by immediate adjuvant treatment. Itch and pain — real features of active keloids — respond as the scar quiets. This pathway runs through Dr Sin Yong's keloid treatment programme; raised acne scarring on the jaw and chest is assessed alongside the atrophic scar types, since many faces carry both directions of scarring at once.

What doesn't work for keloids?

Waiting for a keloid to fade — regression is the exception, expansion the pattern. Scar creams and oils on an established keloid — massage-grade intervention for a structural overgrowth. Cutting it off at a general clinic without an adjuvant plan — the recurrence literature is unambiguous. Home remedies — from apple cider vinegar to thread ligation — which add inflammation to tissue that answers inflammation with growth. And piercing the other ear to 'test' — keloid tendency is systemic; the test result is another keloid.

“Cutting a keloid without an adjuvant plan is offering it a fresh wound — the recurrence isn't bad luck, it's the biology you invited.”

— Dr Sin Yong

Dr Sin Yong’s Viewpoint

The keloid patients I meet have usually been offered the one thing keloids love: excision without a plan. Surgery alone answers a keloid with a fresh wound in keloid-forming skin, and the recurrence statistics are unforgiving. My approach is the evidence ladder — injections, patience, staged decisions — and surgery only ever chaperoned by adjuvant treatment.

Prefer Not to Use WhatsApp?

Use the short enquiry form instead →

Leave your name, mobile number and email and the clinic will contact you directly. No obligation.

Your details are delivered directly to Dr Sin Yong's clinic team.

Thank you — your enquiry has been received. The clinic will contact you during opening hours (Mon–Fri 10am–8pm, Sat 11am–3pm).

Prefer a preliminary view first? You can also WhatsApp a photo of the area for Dr Sin Yong to review before you decide on a visit.

Which type do you have?

Keloids, hypertrophic scars and look-alikes: how they are recognised and managed
Type / look-alikeHow to recognise itWhat it needsWhat does not work
KeloidGrows beyond the wound's borders, rarely regresses, may keep expandingAssessment, then the injection-based ladder; surgery only with adjuvant treatmentWaiting, creams, or excision alone
Hypertrophic scarStays within the wound, peaks, then often settles partlySilicone and pressure, with injections if it persistsAssuming it is harmless without assessment
Fresh raised scarNewly raised and still maturing after injury or surgerySilicone sheeting or gel with pressurePicking, friction and home remedies
Raised acne scar on jaw or chestFirm raised nodules on high-tension skinAssessment alongside atrophic scar types; same ladder if keloidalTreating it as an ordinary acne mark
Keloid recurring after surgeryRegrowth, sometimes larger, after excision aloneReview of history, then a combined adjuvant planRepeating excision without adjuvant treatment

What does not work, and why

When to see a doctor

Myths we hear in clinic

“Keloids fade if you leave them alone.”

Regression is the exception; keloids more often keep expanding for years.

“Cutting a keloid off solves the problem.”

Surgery is a fresh wound in keloid-forming skin, and recurrence after excision alone is the documented norm.

Questions Patients Actually Ask

How do I know if my scar is a keloid or hypertrophic?+

Borders and timeline: a scar confined to the original wound that peaked and is slowly settling is hypertrophic; one growing beyond the wound's footprint months later is a keloid. The distinction changes the treatment plan.

Are keloid injections painful?+

The injection stings briefly — modern technique, fine needles and topical anaesthesia keep it very tolerable, and sessions are minutes long.

How many injection sessions will I need?+

Courses run over months — keloids flatten by degrees, not appointments. Honest plans are stated in courses, and response is reviewed along the way.

Can my keloid be surgically removed?+

Sometimes — but only with immediate adjuvant therapy planned in advance, because excision alone carries documented high recurrence. Surgery is a chapter in a plan, never the whole plan.

Why does my keloid itch and hurt?+

Active keloids are biologically busy — inflamed, growing tissue with its own nerve involvement. Itch and pain typically settle as treatment quiets the scar.

I keloid easily — should I avoid piercings and procedures?+

On high-risk anatomy — earlobes, chest, shoulders, jaw — yes, or proceed only with a prevention plan. Every elective wound in keloid-prone skin deserves a deliberate decision.

What causes keloids and hypertrophic scars?+
Fibroblasts keep laying down collagen after the repair is complete. Genetics sets the tendency, and keloids are markedly more common in Asian and African skin. Tension on the skin and triggers such as piercings, acne, BCG vaccination or minor injury add to the risk, especially on the earlobes, jawline, chest and shoulders.
Can keloids be fully removed?+
Not reliably. Excision alone is a fresh wound in keloid-forming skin and recurrence is the documented norm, so surgery is only considered with immediate adjuvant treatment planned in advance. Injection-based plans soften and flatten scars by degrees rather than at one appointment, and response is reviewed along the way.
Which treatment suits keloids?+
It depends on the type, age, site and size of the scar and your history. Fresh raised scars suit silicone with pressure, established ones suit intralesional corticosteroid, sometimes with 5-fluorouracil, and laser may be added as an adjunct. Excision is reserved and always accompanied by adjuvant treatment.
How much does keloid treatment cost in Singapore?+
The fee depends on the number and size of scars, their site, the medicines and devices used, how long a course is needed to review, and whether laser adjuncts are combined. A written quote is given at consultation after assessment of the borders and history, and the assessment decides whether treatment is advised.

References

  1. The Most Current Algorithms for the Treatment and Prevention of Hypertrophic Scars and Keloids: A 2020 Update — Burns & Trauma (PMC).
  2. Update on Management of Keloid and Hypertrophic Scars: A Systemic Review — Journal of Cosmetic Dermatology (PubMed).

Medically reviewed by Dr Sin Yong, MBBS (NUS), MRCS (Edinburgh) · Last updated 7 September 2026 · Editorial policy

Related reading
Follow Dr Sin Yong
InstagramTikTokYouTubeThreadsXLinkedInFacebook
Printable patient guide (PDF): Acne scar types and options — medically reviewed by Dr Sin Yong.
Dr Sin Yong · Every assessment personally performed
WhatsApp Enquiry